Introduction-
The World Health Organization (WHO) declared the novel coronavirus disease 2019 (COVID-19) global
pandemic on 11 March 2020. Ethiopia reported the first COVID-19 case on 13 March 2020. SARS-CoV-2 and the
resulting COVID-19 pandemic present important diagnostic challenges. The coronavirus 2019 pandemic could
be managed with the aid of error-free, quick diagnostic tests for SARS-CoV2 infection. While COVID-19 and
malaria can present similarly, they often share symptoms.
Rapid Antigen Test for COVID-19-
Rapid antigen tests (RATs) are the testing for coronavirus disease 2019 also name as COVID-19. They
are very accurate and quick, if someone has any symptoms or has been in contact with person who has COVID
19. Rapid antigen tests discover the proteins of the virus that lead to coronavirus. It can take 3 to 7 days after
that suppuration for there to be as necessary antigen to be discovered by the test.
The SARS-CoV-2 Rapid Antigen Test is a rapid chromatographic immunoassay. It is for the qualitative
detection of specific antigen of SARS-CoV-2 present in the human nasopharyngeal or merged nasopharyngeal /
oropharyngeal specimens. This outcome is strictly planned for full time use in laboratory and points of
protection surroundings.
The SARS-CoV-2 virus result in respiratory tract. It is transfer mainly via respiratory droplets after
intimacy and primary viral replication is presumed to occur in mucosal epithelium of the upper respiratory
tract. At this position viral fill up peaks within the first week after symptom onset, and then decreases. A SARS
CoV-2 antigen test identify the presence of the SARS-CoV-2 virus from part of the upper respiratory tract sspecimens by recognizing a nucleoprotein that is controlled by the virus. The test identifies present infection
during the acute phase of COVID -19, while the virus is occurring in large amount in the respiratory tract.
Benefits and features of the SARS-CoV-2 Rapid Antigen Test-
Besides laboratory PCR testing, antigen assays can also be provided as rapid testing in near victim
surroundings. It can therefore be used to assess whether a person is infected with SARS-CoV-2 by providing a
qualitative result showing colored bands demonstrating the presence of SARS-CoV-2 antigen. The SARS-CoV-2
Rapid Antigen Test enables fast results, and it uses for screening of individuals after confirmed exposure to a
SARS-CoV-2 infected person or separates at risk of exposure. The SARS-CoV-2 Rapid Antigen Test allows for
decentralized testing at the point of care and assists to enlarge the range and quantity of direct viral testing
into otherwise uncontrollable locations. Rapid point of care testing can sometimes be the only viable chance if
lab testing is not sufficiently possible. In addition to that, the SARS-CoV-2 Rapid Antigen Test is an instrument
free test, allowing testing in rural/ low-infrastructure areas.
Rapid Diagnostic Test for Malaria-
Rapid diagnostic tests (RDTs) frequently use a dipstick or cassette pattern and give results in about 20 minutes.
A blood example composed from the tolerant is put into the sample pad on the test card along with certain
reagents. Nowadays agree to RDTs for produce in the malaria-endemic world can determine 2 types of malaria
antigens; one is specific for P. falciparum and the second one is found in all 4 human species of malaria. After
15 to 20 minutes (depending on the test), the presence of bands in the test card window shows whether the
patient is infected with P. falciparum or one of the other 3 species of human malaria.
Rapid diagnostic tests (RDTs) provide a functional different to microscopy in situations where
inevitable microscopic diagnosis is unavailable—or is unavailable right away. This is the case in most of the
malaria-endemic world. Malaria RDTs are being broadly used in malaria-endemic countries, but the use of an
RDT does not retire the need for malaria microscopy. Because RDTs may be incapable to determine some
infections with few of malaria parasites in the patient’s blood and the not as much familiar species of
malaria, P. ovale and P. malariae, in the malaria-endemic world.
Case Report-:
Article tittle – CIVID-19 and Malaria coinfection in an Ethiopian middle-aged woman presenting with bilateral
pleural effusion and acute febrile illness.
Journal tittle- Journal of Medical Case Reports
Indexing details- Scopus and PubMed
Patient description –
This is a 57-year-old black Ethiopian female patient who presented to the emergency department
(ED) of Yakutat 12 Hospital Medical College with fever, chills, and headache of a week duration associated with
fatigue, shortness of breath, and dry cough.
Case history –
57-year-old Ethiopian woman who admitted to the emergency department (ED) of Hospital Medical
College with fever, chills, and headache of a week duration related with fatigue, shortness of breath, and dry
cough. Tree days prior to her presentation, she begun to expand diarrhea, which subsided after her visit to our
hospital. She had recent travel history to a malaria-endemic area. Upon physical test she had fever,
hypotension, tachycardia, tachypnea, oxygen desaturation to the level of 70% with room air, and decreased air
entry and dullness over the lower one-third of the chest bilaterally. Our patient had journey history to a
malaria-endemic zone and her peripheral blood smear manifested Plasmodium falciparum.
Clinical and Physical examination results –
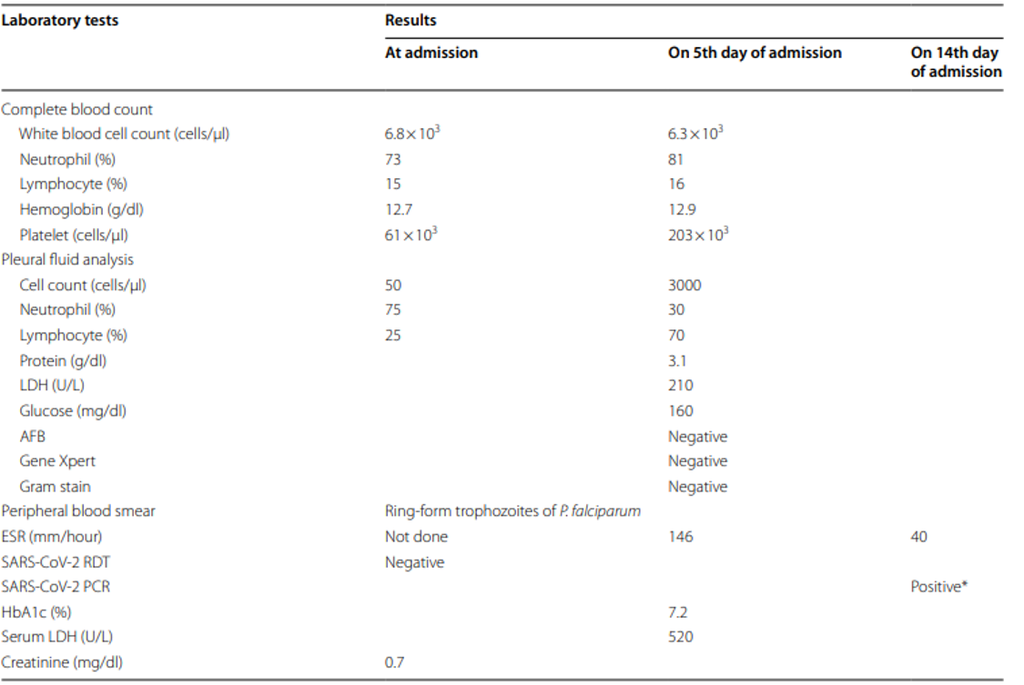
On laboratory testing, complete blood count revealed mild lymphopenia (1000 cells/µl); peripheral
blood smear revealed ring-form trophozoites of Plasmodium falciparum; renal and liver function tests were
within normal ranges; initial pleural fluid analysis was serous with total cell count of 50 cells/µl, which
increased to 3000 cells/µl (lymphocyte of 70%) with serous appearance, and nonremarkable protein, glucose,
and LDH levels; erythrocyte sedimentation rate (ESR) was initially 146 mm/hour, which then dropped to
40 mm/hour on her 14th day of admission. Serial chest X-rays showed symmetrical bilateral pleural effusion at
presentation, left-side predominant bilateral pleural effusion on the 5th day of admission, and significant
improvement on the 14th day of admission. Chest computed tomography (CT) with contrast revealed bilateral
ground-glass opacities and consolidations involving all lung zones with bilateral moderate pleural effusions.
Echocardiography revealed mild left ventricular hypertrophy (LVH) with grade I diastolic dysfunction. On the
5th day of ward admission, control chest X-ray showed bilateral pleural effusion with left side predominance.
Repeat pleural fluid analysis manifested increased cell count (3000 cells/µl) with lymphocytic predominance
(70%), and pleural fluid cytology manifested no malignant cells.
Method and results relevant to the selected test –
Rapid Antigen Test for SARS-CoV-2 was negative at her presentation to the ED. After reconsider of
the patient, viral cause like COVID-19 was erased again and done again testing with SARS-CoV-2 PCR was done
and turned out to be positive. The diagnosis of COVID-19 was initially ruled out for the patient upon her
presentation at the emergency department due to the negative rapid antigen test for SARS-CoV-2, positive
blood smear for Plasmodium falciparum, and chest X-ray revealing bilateral pleural effusion, which did not
support a COVID-19 diagnosis. However, after admission to the medical ward, her findings could not be
explained by a plausible diagnosis and COVID-19 test was done again with SARS-CoV-2 PCR and it turned out to
be positive. Due to the SARS-CoV-2 fast antigen test’s inferior diagnostic accuracy for COVID 19, relying solely
on these tests could result in a sizable percentage of people being mistakenly recognized as SARS-CoV-2
negative. The use of Real Time Polymerase Chain Reaction (RT-PCR) to detect SARS-CoV-2 nucleic acid in
sputum or throat swabs and lower respiratory tract secretions for patients with felt SARS-CoV-2 infection
become visible obligatory for diagnosis, in addition to clinical and radiological symptoms. According to a
systematic analysis of 23 studies, the mean prevalence of pleural effusion in patients with COVID-19 is 9.55%
and the presence of pleural effusion is linked with a higher severity of disease.
Results of other investigations –
PCR testing for COVID-19 after admission to the medical ward turned out to be positive.
Treatment plan / Expected outcome / Follow up details.
she was placed on intranasal oxygen, resuscitated with intravenous fluid and was begun on intravenous
artesunate. After admission to the medical ward, intravenous artesunate was replaced to oral artemether
lumefantrine; ceftriaxone with azithromycin and diuresis were begun for consideration of both pneumonia
with parapneumonic effusion and heart failure respectively. Despite optimal diuresis and the antibiotics, her
respiratory condition was not upgraded and for this reason, antibiotics were changed to cefepime, and
vancomycin and chest CT angiography was also done suggesting multifocal pneumonia with bilateral
parapneumonic effusion. On the 10th day of the patient’s admission, her condition began to improve,
accompanied by a decreased oxygen need and a drop in ESR to 116 mm/hour. On the 14th day of her
admission, ESR decreased further to 40 mm/hour and follow-up chest X-ray showed a notable radiologic
improvement. Her final diagnosis was newly determined type 2 diabetes mellitus, Plasmodium falciparum
malaria, and COVID-19 pneumonia with parapneumonic effusion. She was discharged with noticeable
improvement and upon serial evaluations at the outpatient department on her 1st and 3rd week of discharge,
her symptoms had vanished except for mild fatigue and physical examination was also non-remarkable. The
low incidence of COVID-19 in malaria endemic nations has been allocated to angiotensin-converting enzyme 2
(ACE2), hydroxychloroquine (HCQ) and chloroquine (CQ), interferons, and neutralizing antibodies. In a
retrospective cohort study of 591 patients with an established diagnosis of COVID-19, the coinfection rate with
malaria was 45.7% and the maximum of malaria patients (51.9%) were infected with Plasmodium falciparum.
edCOVID-19 cases with and without concurrent malaria had crude death rates of 10.71 and 5.87 per 1000
person-days in the same study, respectively. Suitable diagnostic investigations for both COVID-19 and malaria
should be done for any patient presenting with respiratory complaints and symptoms of acute febrile illness in
malaria-endemic areas.
References –
Gashaw Solela 1, Addis Aschenek 2, Mikale Dawit 2, Getachew Wondafrash 3 Affiliations 1 Department of
Internal Medicine, Yekatit 12 Hospital Medical College, Addis Ababa, Ethiopia. gashawsol@gmail.com. 2
Department of Internal Medicine, Yekatit 12 Hospital Medical College, Addis Ababa, Ethiopia.
https://pubmed.ncbi.nlm.nih.gov/37649108
0 Comments